

 Please Scroll Down to See Forums Below















You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Ross, important question for you!
- Thread starter jnef
- Start date

njmuscleguy
New member
Is this just for Ross to answer or can anyone else chime in?

njmuscleguy said:Is this just for Ross to answer or can anyone else chime in?
Go for it. I was about to do the same thing myself. My keyboard was itching...lol.


jnef
New member
GUARDIAN said:Go for it. I was about to do the same thing myself. My keyboard was itching...lol.
lol its for everybody - i asked him in a pm and he wanted me to title it that and post it so he could answer on the forum.

digitizedsoul
New member
I'm not ross, but I will express my humble attempt at an educated answer:
All those compounds are suppressive. So in essence you shut down natural test production, and don't supplement with outside sources of it during that time.
It's like your boss firing you, but saying "its ok bro, i'll give you 5000$ a week untill I hire you back"
Now by using compounds that are suppresive, without the test, its like your boss firing you but not offering to give you ANYTHING. So you get kicked out, no "normal" income, and it isn't replaced with anything else.
Again this is simply my humble attempt at a response
All those compounds are suppressive. So in essence you shut down natural test production, and don't supplement with outside sources of it during that time.
It's like your boss firing you, but saying "its ok bro, i'll give you 5000$ a week untill I hire you back"
Now by using compounds that are suppresive, without the test, its like your boss firing you but not offering to give you ANYTHING. So you get kicked out, no "normal" income, and it isn't replaced with anything else.
Again this is simply my humble attempt at a response
jnef
New member
JNEF said:lol its for everybody - i asked him in a pm and he wanted me to title it that and post it so he could answer on the forum.
you guys are good bros and would love to hear what you guys have to say.
btw ive always ran test just because i know i should have it in my body - synthetic or not. just curious to the big reasons on why aside from ed.
njmuscleguy
New member
well, this is my take on it....practically every AAS compound one could run is going to shut down natural test, so it's important to at LEAST supply exogenously the amount of test the body would be making naturally. Something like tren or masteron is not a substitute for what test can do. Of course, most people run much higher dosages of test than the body "needs", simply for it's anabolic/androgenic benefits.
Test has a host of other benefits besides ensuring against ED... if you were deficient in natural test, then you'd know what I'm talking about (lethargy, lack of focus, lipids would be off, overall health and sense of well-being would decrease).
Test has a host of other benefits besides ensuring against ED... if you were deficient in natural test, then you'd know what I'm talking about (lethargy, lack of focus, lipids would be off, overall health and sense of well-being would decrease).
jnef
New member
digitizedsoul said:I'm not ross, but I will express my humble attempt at an educated answer:
All those compounds are suppressive. So in essence you shut down natural test production, and don't supplement with outside sources of it during that time.
It's like your boss firing you, but saying "its ok bro, i'll give you 5000$ a week untill I hire you back"
Now by using compounds that are suppresive, without the test, its like your boss firing you but not offering to give you ANYTHING. So you get kicked out, no "normal" income, and it isn't replaced with anything else.
Again this is simply my humble attempt at a response
thanks for the response - now curious to what the negs would be with not running it. what will a lack of test do?

chazk
New member
JNEF said:hey ross...whay is it so important to run test in every cycle? aside from ed being the obvious.
If one was to run something along the lines of mast/tren/halo what would be the downfall?
I thought ross just posted a no test cycles were the way to go to avoid shut down?

jnef
New member
so would running just 200mgs week keep my body "regular" while say running 100mg para/100mg mast ednjmuscleguy said:well, this is my take on it....practically every AAS compound one could run is going to shut down natural test, so it's important to at LEAST supply exogenously the amount of test the body would be making naturally. Something like tren or masteron is not a substitute for what test can do. Of course, most people run much higher dosages of test than the body "needs", simply for it's anabolic/androgenic benefits.
Test has a host of other benefits besides ensuring against ED... if you were deficient in natural test, then you'd know what I'm talking about (lethargy, lack of focus, lipids would be off, overall health and sense of well-being would decrease).
njmuscleguy
New member
JNEF said:so would running just 200mgs week keep my body "regular" while say running 100mg para/100mg mast ed
ABSOLUTELY! In fact, HRT (hormone replacement therapy) dosage of test in most cases is 100-150mg per week. So if you're taking 150-200mg, then you're definitely ensuring that you're supplying what your body would be making naturally (that is, if you're healthy and have no hormonal deficiencies).
Over the years, dosages of *all* AAS have drastically increased... people think that you need alot more in order to get any kind of results. Simply not true. You can still get great results at lower, more modest dosages provided your training and diet are in check.
jnef
New member
njmuscleguy said:ABSOLUTELY! In fact, HRT (hormone replacement therapy) dosage of test in most cases is 100-150mg per week. So if you're taking 150-200mg, then you're definitely ensuring that you're supplying what your body would be making naturally (that is, if you're healthy and have no hormonal deficiencies).
Over the years, dosages of *all* AAS have drastically increased... people think that you need alot more in order to get any kind of results. Simply not true. You can still get great results at lower, more modest dosages provided your training and diet are in check.
thanks for the answer
so heres my next question. why is always said "run test higher then the other aas" if 200 will keep me "normal" why bother bumping it above the other aas?

Great question, let's adress the "Testosterone Myth".JNEF said:hey ross...whay is it so important to run test in every cycle? aside from ed being the obvious.
If one was to run something along the lines of mast/tren/halo what would be the downfall?
Testosterone is frequently used as the BASE of all steroid cycles, providing an equal amount of anabolic and androgenic support throughout the duration of the cycle. Testosterone does not have to be the base of every cycle, but it SHOULD be the base of almost every cycle, and for several very important reasons:
First of all, Testosterone maintains a good mood, a strong libido, and healthy levels of energy. Failure to utilize Testosterone will result in a decreased libido, level of energy and quality of mood. This is because the body has ceased all(or most) endogenous(natural) testosterone production, as the HPTA is inhibited.
Secondly, Testosterone is SYNERGISTIC. Adding even a MINIMAL dosage of Testosterone to ANY cycle will completely enhance the effects. For most cycles, adding Testosterone is a no-brainer.
However, one can still run a very successful cycle without Testosterone, by simply using Proviron or Masteron as an androgenic replacement. Proviron and Masteron will both counteract the side-effects associated with low testosterone levels, by adding a distinct and powerful androgenic component to your cycle. For example, one could run Trenbolone/Masteron/Proviron or Deca/Dianabol/Proviron and still maintain a healthy libido without Testosterone.
Here are some NON-Test cycles:
BULKING
Weeks 1-6: Dianabol, 40mgs ED
Weeks 1-8: Proviron, 50mgs
Weeks 1-8: Tren A, 100mgs EOD
Weeks 1-6: Dianabol, 40mgs ED
Weeks 1-10: Deca, 400mgs
Weeks 1-10: Proviron, 50mgs ED
Weeks 8-14: Winstrol, 50mgs ED
CUTTING
Weeks 1-8: Masteron, 100mgs EOD
Weeks 1-8: Anavar, 40mgs ED
Weeks 1-8: Winstrol Inject, 50mgs EOD
Weeks 1-10: Primobolan
Weeks 1-10: Proviron, 50mgs ED
Weeks 1-10: Turinabol, 50mgs ED
JNEF said:thanks for the answer
so heres my next question. why is always said "run test higher then the other aas" if 200 will keep me "normal" why bother bumping it above the other aas?
Complete nonsense.
jnef
New member
Ross said:Great question, let's adress the "Testosterone Myth".
Testosterone is frequently used as the BASE of all steroid cycles, providing an equal amount of anabolic and androgenic support throughout the duration of the cycle. Testosterone does not have to be the base of every cycle, but it SHOULD be the base of almost every cycle, and for several very important reasons:
First of all, Testosterone maintains a good mood, a strong libido, and healthy levels of energy. Failure to utilize Testosterone will result in a decreased libido, level of energy and quality of mood. This is because the body has ceased all(or most) endogenous(natural) testosterone production, as the HPTA is inhibited.
Secondly, Testosterone is SYNERGISTIC. Adding even a MINIMAL dosage of Testosterone to ANY cycle will completely enhance the effects. For most cycles, adding Testosterone is a no-brainer.
However, one can still run a very successful cycle without Testosterone, by simply using Proviron or Masteron as an androgenic replacement. Proviron and Masteron will both counteract the side-effects associated with low testosterone levels, by adding a distinct and powerful androgenic component to your cycle. For example, one could run Trenbolone/Masteron/Proviron or Deca/Dianabol/Proviron and still maintain a healthy libido without Testosterone.
Here are some NON-Test cycles:
BULKING
Weeks 1-6: Dianabol, 40mgs ED
Weeks 1-8: Proviron, 50mgs
Weeks 1-8: Tren A, 100mgs EOD
Weeks 1-6: Dianabol, 40mgs ED
Weeks 1-10: Deca, 400mgs
Weeks 1-10: Proviron, 50mgs ED
Weeks 8-14: Winstrol, 50mgs ED
CUTTING
Weeks 1-8: Masteron, 100mgs EOD
Weeks 1-8: Anavar, 40mgs ED
Weeks 1-8: Winstrol Inject, 50mgs EOD
Weeks 1-10: Primobolan
Weeks 1-10: Proviron, 50mgs ED
Weeks 1-10: Turinabol, 50mgs ED
thanks ross was wondering when you were going to chime in lol
njmuscleguy
New member
JNEF said:thanks for the answer
so heres my next question. why is always said "run test higher then the other aas" if 200 will keep me "normal" why bother bumping it above the other aas?
Well, *they* say that because the theory is the higher dosage of test will compensate for the side effects caused by the accompanying compound... deca is a classic case... deca causes libido issues, so people recommend running a higher dosage of test than deca to deal with the "deca dick" issue... I can't really prove or disprove if it's absolutely necessary to do this (run higher test)... some might need it, others might not
jnef
New member
njmuscleguy said:Well, *they* say that because the theory is the higher dosage of test will compensate for the side effects caused by the accompanying compound... deca is a classic case... deca causes libido issues, so people recommend running a higher dosage of test than deca to deal with the "deca dick" issue... I can't really prove or disprove if it's absolutely necessary to do this (run higher test)... some might need it, others might not
gotcha so that goes back to the ed issue
couldnt that also be combated with keeping normal test doses and throwing in cabaser/dostinex which would also help keep the prolactin levels in reason
JNEF said:gotcha so that goes back to the ed issue
couldnt that also be combated with keeping normal test doses and throwing in cabaser/dostinex which would also help keep the prolactin levels in reason
It is simply fasle logic;
People assume that to counteract the 400mgs of Deca you need 400mgs of Testosterone, which is simply NOT TRUE.
200mgs of Testosterone is more than enough to keep you raging on 400mgs of Deca.

Well, I don't think test is necessary for a beginner. A first timer can make good gains with something mildly suppressive like Primo. Adding test will just make recovery harder.
JNEF said:the bros here on ef f***in rock, i do my research but still have questions at the end of the day - you guys always answer em without being dicks. just wanted to say thanks
Glad we can help! EF4LIFE BABY!
jnef
New member
Ross said:By the way, Masteron/Trenbolone/Halotestin is a SICKKKKK cutting cycle!!
have you run it ross? what did it do for you?
JNEF said:have you run it ross? what did it do for you?
Masteron/Halo/Primo is what I run because I do not use Trenbolone, but adding Trenbolone in your case would produce UNBELIEVABLE results!
Insane vascularity, hardness, definition and striations--you will look and FEEL like a piece of STEEL! You will also have superhuman STRENGTH.
jnef
New member
JNEF said:have you run it ross? what did it do for you?
btw when do you recomend taking the halo.. with the am inject ( i would run ed injects) however i workout around 5 or so. split the dose up maybe? id be running 40mg ed
JNEF said:btw when do you recomend taking the halo.. with the am inject ( i would run ed injects) however i workout around 5 or so. split the dose up maybe? id be running 40mg ed
40mgs ED is ALOT, trust me!!
Start with 10mgs taken twice per day, giving you 20mgs total ED.
INSANE STRENGTH and HARDNESS!!!!
jnef
New member
so you felt no downsides with not running test in that cycle...ie no lethargy or bad moodRoss said:Masteron/Halo/Primo is what I run because I do not use Trenbolone, but adding Trenbolone in your case would produce UNBELIEVABLE results!
Insane vascularity, hardness, definition and striations--you will look and FEEL like a piece of STEEL!
JNEF said:so you felt no downsides with not running test in that cycle...ie no lethargy or bad mood
The addition of Masteron maintained my libido, mood, and energy. Halotestin has a similar effect as well, so on that particular cycle I was fine.
REMEMBER, if you don't use testosterone, you MUST use either Proviron or Masteron as an Androgenic replacement!
Nelson Montana said:Well, I don't think test is necessary for a beginner. A first timer can make good gains with something mildly suppressive like Primo. Adding test will just make recovery harder.
I agree...kind of.

Tatyana
Elite Mentor
Someone explain this to me.
According to Bill Llewellyn, all steroids are based off one of three compounds, test, DHT and think it is pregnalone.
They are all derived from cholesterol and share the same five ring structure with just variable double bonds and side chains.
When you look at pics of the various steroids, they all follow the same pattern.
This is so they will fit into the androgen/testosterone receptor.
No binding with the receptor (and this sort of works like a lock and key principle), no 'switching' on of the DNA protein making machine.
Cause that is what hormones do, they are 'chemical messengers' to tell the cells to do things. THEY don't actually produce the result directly.
So if a steroid has to bind to a receptor to work, it has to be similar to test, so how can adding test make any difference?
They are still stimulating the same receptor (well there are two isoforms).
The structure only changes the pharmocodynamics, which is REALLY complicated and I would have to read more to refresh my really basic knowlege on it.
According to Bill Llewellyn, all steroids are based off one of three compounds, test, DHT and think it is pregnalone.
They are all derived from cholesterol and share the same five ring structure with just variable double bonds and side chains.
When you look at pics of the various steroids, they all follow the same pattern.
This is so they will fit into the androgen/testosterone receptor.
No binding with the receptor (and this sort of works like a lock and key principle), no 'switching' on of the DNA protein making machine.
Cause that is what hormones do, they are 'chemical messengers' to tell the cells to do things. THEY don't actually produce the result directly.
So if a steroid has to bind to a receptor to work, it has to be similar to test, so how can adding test make any difference?
They are still stimulating the same receptor (well there are two isoforms).
The structure only changes the pharmocodynamics, which is REALLY complicated and I would have to read more to refresh my really basic knowlege on it.
You bring up some very good intelligent questions Tat. If u dont receive the answers u are looking for pm me and i may have a source that can answer them.
Tatyana said:Someone explain this to me.
According to Bill Llewellyn, all steroids are based off one of three compounds, test, DHT and think it is pregnalone.
They are all derived from cholesterol and share the same five ring structure with just variable double bonds and side chains.
When you look at pics of the various steroids, they all follow the same pattern.
This is so they will fit into the androgen/testosterone receptor.
No binding with the receptor (and this sort of works like a lock and key principle), no 'switching' on of the DNA protein making machine.
Cause that is what hormones do, they are 'chemical messengers' to tell the cells to do things. THEY don't actually produce the result directly.
So if a steroid has to bind to a receptor to work, it has to be similar to test, so how can adding test make any difference?
They are still stimulating the same receptor (well there are two isoforms).
The structure only changes the pharmocodynamics, which is REALLY complicated and I would have to read more to refresh my really basic knowlege on it.
Tatyana said:Someone explain this to me.
According to Bill Llewellyn, all steroids are based off one of three compounds, test, DHT and think it is pregnalone.
They are all derived from cholesterol and share the same five ring structure with just variable double bonds and side chains.
When you look at pics of the various steroids, they all follow the same pattern.
This is so they will fit into the androgen/testosterone receptor.
No binding with the receptor (and this sort of works like a lock and key principle), no 'switching' on of the DNA protein making machine.
Cause that is what hormones do, they are 'chemical messengers' to tell the cells to do things. THEY don't actually produce the result directly.
So if a steroid has to bind to a receptor to work, it has to be similar to test, so how can adding test make any difference?
They are still stimulating the same receptor (well there are two isoforms).
The structure only changes the pharmocodynamics, which is REALLY complicated and I would have to read more to refresh my really basic knowlege on it.
True , all steroids are based on the T molecule, but some impart more than others and since any exogenous T is suppressive, some wind up lowering T instead of elevating it. (Technically, this is a different pathway with nandrolones, but that's another story). All steroids also increase nitrogen, which is essentially what grows muscle and what makes Primo so coveted. It does so with less androgenic influx. The problem is, as you inferred, it's still going to suppressive, albeit slightly. So some people will add test to "kick it up."
Meanwhile, the increased androgen from something as basic as test increases strength and water retention which leads to increased muscle size -- IF -- the person makes the most of it. I'd say 90% of the people who like test do so because it works fast, increases strength, mood and libido, swells you up with water and gives the impression of "gains." And it's cheap. But a drug like Primobolan will be more subtle yet increase actual muscle tissue to a greater degree. (Remember, a pound of muscle tissue is quite a bit but will not change appearance as much as 10 pounds of water and increased blood volume).
Having said all that, I think the differences in steroids is sometimes overanalyzed. They all do the same thing. Some do it a little more effectively and a little less harshly than others, depending on your preference.
Last edited:
njmuscleguy
New member
Tatyana said:This is so they will fit into the androgen/testosterone receptor.
No binding with the receptor (and this sort of works like a lock and key principle), no 'switching' on of the DNA protein making machine.
So if a steroid has to bind to a receptor to work, it has to be similar to test, so how can adding test make any difference?
Tatyana, let me see if I'm understanding your question (it's early)... are you asking that if an accompanying AAS compound that in theory is similar to test is already binding the receptors, then of what benefit is it to add test on top of that?
I know I can't readily answer that with any medical / scientific evidence... and I can't really answer that by experience or "FEEL" since I always run test in any of my cycles. So I can't compare it to a cycle *without test*.
However, if there was no benefit of running test along with say tren, or deca, or primo, etc. etc. etc., then why would countless people over the years be doing it? Why do people say "primo is enhanced when running test" or "proviron and test are syngergistic". Now that I think of it, primo and proviron are dht-derivitives and test is, well test... so I guess they each bind to different receptors? Forgive my ignorance, just thinking out loud
Tatyana
Elite Mentor
I am at work, and working on my research project, I will read the responses more carefully when I get home.
BUT, I did make a few boo-boos.
Testosterone is a 4 ring molecule.
I think the three basic forms of test are test, dihydrotest and dihydroepiandrosterone.
Most of my stuff is with the pathology of endocrinology, so what goes wrong, and only the basics of the normal physiology.
It is rather involved.
BUT, I did make a few boo-boos.
Testosterone is a 4 ring molecule.
I think the three basic forms of test are test, dihydrotest and dihydroepiandrosterone.
Most of my stuff is with the pathology of endocrinology, so what goes wrong, and only the basics of the normal physiology.
It is rather involved.

gjohnson5
New member
I think this is a good start to the question.
I will try to explain this as best as I can, because this won't be a very good explanation...
What we need to look at is where the androgen receptor is located and androgen-dependant gene expression. When an androgen attaches to an androgen receptor, that androgen act son certain functions in the body and this can be dependant on what type of androgen attached to the androgen receptor. Also the type of physiological change from that androgen attahching to the androgen receptor will also depend on what type of cell that androgen receptor was located on. Steroid hormones (or lack of steroid hormones) can cause different physiological changes in muscle , bone , nerve, gland and organ tissue.
The easiest way for me to demonstrate this is by using ATD as an example. The location with the highest number of androgen receptors is the hypothalamus gland. One of it's purposes it to regulate androgen production from other hormones. When ATD (which has a higher affinity for those same receptors as testosterone) attaches to those androgen receptors the function that ATD carries out on those receptors does not initiate the sequence of events which lead to reduces if not completely stopped production GrNH. The ATD androgen itself is too weak an androgen to trigger the sequence of events in the hypothalamus which leads to shutdown. The expression that which androgen initiates is different then other androgens which attach to the AR's of the hypothalamus. Hence ATD is used to "trick" the hypothalamus into thinking there are less circulating androgens in your blood then there really are. But there is a cost associated with ATD attaching to androgen receptors in other parts of the body then a "real" androgen
The expression initiated by testosterone attaching to muscle is different then say a 19-nor-testosterone molecule. Also this expression is different if the androgen attaches to bone or nerve or the testes. So what we would need to look at is the sequence of events which take place after testosterone attaches to AR's in muscle as compared to a DHT like drug such as masteron. This is why we'd listen to bodybuilders because they would have more anectdotal answers to these questions, where as a scientists would need to study this in a lab setting as well as injecting someone with the chemicals if they are doing a human study.
Hopefully I didn't fuck up too bad
I will try to explain this as best as I can, because this won't be a very good explanation...
What we need to look at is where the androgen receptor is located and androgen-dependant gene expression. When an androgen attaches to an androgen receptor, that androgen act son certain functions in the body and this can be dependant on what type of androgen attached to the androgen receptor. Also the type of physiological change from that androgen attahching to the androgen receptor will also depend on what type of cell that androgen receptor was located on. Steroid hormones (or lack of steroid hormones) can cause different physiological changes in muscle , bone , nerve, gland and organ tissue.
The easiest way for me to demonstrate this is by using ATD as an example. The location with the highest number of androgen receptors is the hypothalamus gland. One of it's purposes it to regulate androgen production from other hormones. When ATD (which has a higher affinity for those same receptors as testosterone) attaches to those androgen receptors the function that ATD carries out on those receptors does not initiate the sequence of events which lead to reduces if not completely stopped production GrNH. The ATD androgen itself is too weak an androgen to trigger the sequence of events in the hypothalamus which leads to shutdown. The expression that which androgen initiates is different then other androgens which attach to the AR's of the hypothalamus. Hence ATD is used to "trick" the hypothalamus into thinking there are less circulating androgens in your blood then there really are. But there is a cost associated with ATD attaching to androgen receptors in other parts of the body then a "real" androgen
The expression initiated by testosterone attaching to muscle is different then say a 19-nor-testosterone molecule. Also this expression is different if the androgen attaches to bone or nerve or the testes. So what we would need to look at is the sequence of events which take place after testosterone attaches to AR's in muscle as compared to a DHT like drug such as masteron. This is why we'd listen to bodybuilders because they would have more anectdotal answers to these questions, where as a scientists would need to study this in a lab setting as well as injecting someone with the chemicals if they are doing a human study.
Hopefully I didn't fuck up too bad
Nelson Montana said:True , all steroids are based on the T molecule, but some impart more than others and since any exogenous T is suppressive, some wind up lowering T instead of elevating it. (Technically, this is a different pathway with nandrolones, but that's another story). All steroids also increase nitrogen, which is essentially what grows muscle and what makes Primo so coveted. It does so with less androgenic influx. The problem is, as you inferred, it's still going to suppressive, albeit slightly. So some people will add test to "kick it up."
Meanwhile, the increased androgen from something as basic as test increases strength and water retention which leads to increased muscle size -- IF -- the person makes the most of it. I'd say 90% of the people who like test do so because it works fast, increases strength, mood and libido, swells you up with water and gives the impression of "gains." And it's cheap. But a drug like Primobolan will be more subtle yet increase actual muscle tissue to a greater degree. (Remember, a pound of muscle tissue is quite a bit but will not change appearance as much as 10 pounds of water and increased blood volume).
Having said all that, I think the differences in steroids is sometimes overanalyzed. They all do the same thing. Some do it a little more effectively and a little less harshly than others, depending on your preference.
AR-binding is only one pathway for anabolism, some steroids(such as Dianabol) barely bind to the A-R at all and yet are still extremely anabolic.Tatyana said:Someone explain this to me.
According to Bill Llewellyn, all steroids are based off one of three compounds, test, DHT and think it is pregnalone.
They are all derived from cholesterol and share the same five ring structure with just variable double bonds and side chains.
When you look at pics of the various steroids, they all follow the same pattern.
This is so they will fit into the androgen/testosterone receptor.
No binding with the receptor (and this sort of works like a lock and key principle), no 'switching' on of the DNA protein making machine.
Cause that is what hormones do, they are 'chemical messengers' to tell the cells to do things. THEY don't actually produce the result directly.
So if a steroid has to bind to a receptor to work, it has to be similar to test, so how can adding test make any difference?
They are still stimulating the same receptor (well there are two isoforms).
The structure only changes the pharmocodynamics, which is REALLY complicated and I would have to read more to refresh my really basic knowlege on it.
In terms of HPTA inhibition, each steroid has different binding affinity for the Androgen/Estrogen/Progesterone receptors. Steroids which ACTIVATE these receptors(bind) cause greater HPTA inhibition than those that do not.
gjohnson5
New member
Another example is hair growth /loss
Hair loss is said to be triggered by an androgen DHT attaching to AR in hair follicle.
The exact opposite would be testosterone attaching to AR in hair follicle causing hair growth
So yes , the type of androgen and where the AR is located will determine which expression is initiated
Hair loss is said to be triggered by an androgen DHT attaching to AR in hair follicle.
The exact opposite would be testosterone attaching to AR in hair follicle causing hair growth
So yes , the type of androgen and where the AR is located will determine which expression is initiated
digitizedsoul
New member
This is one of the most mind excercising and educational threads I have ever seen in my time here.
Tat especially but the rest of you as well are displaying knowledge of chemistry / biochemistry that just amazes me. I commend you all for pursuing such complicated wisdom.
I only wish I could contribute, however my knowledge is rather limited on the subject, although so far I have been able to follow along.
Tat especially but the rest of you as well are displaying knowledge of chemistry / biochemistry that just amazes me. I commend you all for pursuing such complicated wisdom.
I only wish I could contribute, however my knowledge is rather limited on the subject, although so far I have been able to follow along.

Harleymarleybone
New member
JNEF said:thanks for the response - now curious to what the negs would be with not running it. what will a lack of test do?
I am not convinced you need test in every cycle. The fact that any steroid suppresses test, does not mean you need to replace it with test, since the steroid you are taking, including the ones you mentioned may be structurally and functionally similar enough to test to do everything that test does, including keeping Mr. Willy happy.
gjohnson5
New member
[The word deca was replaced with the word nandrolone]
Let's talk about nandrolone for a second.
*edit --- I forgot about the structure point*
nandrolone is a 19-nor-testosterone based drug That means that the main difference is that nandrolone and testosterone is that the carbon atom removed from the 19th position of the molecule. So structurally testosterone and nandrolone are very similar. However the expression initiated in the body and the metabolism of the two molecules is dissimilar enough that I would say nandrolone is not a replacement for testosterone. Infact your body sees nandrolone as a progestin instead of a testosterone derivative --- edit*
nandrolone is supressive to the point that noone really runs nandrolone without test. Can anyone point out a compound which can be stacked with nandrolone which can serve as a replacement for test?
*edit EQ maybe?? *edit*
IMHO it's not about replacing test , it's more about using drugs which create the best synergy when stacked. So No , test is not a requirement , but your gains may not be all that great without it
Let's talk about nandrolone for a second.
*edit --- I forgot about the structure point*
nandrolone is a 19-nor-testosterone based drug That means that the main difference is that nandrolone and testosterone is that the carbon atom removed from the 19th position of the molecule. So structurally testosterone and nandrolone are very similar. However the expression initiated in the body and the metabolism of the two molecules is dissimilar enough that I would say nandrolone is not a replacement for testosterone. Infact your body sees nandrolone as a progestin instead of a testosterone derivative --- edit*
nandrolone is supressive to the point that noone really runs nandrolone without test. Can anyone point out a compound which can be stacked with nandrolone which can serve as a replacement for test?
*edit EQ maybe?? *edit*
IMHO it's not about replacing test , it's more about using drugs which create the best synergy when stacked. So No , test is not a requirement , but your gains may not be all that great without it
Harleymarleybone said:I am not convinced you need test in every cycle. The fact that any steroid suppresses test, does not mean you need to replace it with test, since the steroid you are taking, including the ones you mentioned may be structurally and functionally similar enough to test to do everything that test does, including keeping Mr. Willy happy.
Last edited:
njmuscleguy
New member
Harleymarleybone said:I am not convinced you need test in every cycle. The fact that any steroid suppresses test, does not mean you need to replace it with test, since the steroid you are taking, including the ones you mentioned may be structurally and functionally similar enough to test to do everything that test does, including keeping Mr. Willy happy.
what other AAS are you suggesting that is "structurally and functionally similar enough to test" that you wouldn't need TEST? if you say DHT-derivitatves such as proviron and masteron, which are more androgenic than test (but not quite as anabolic), well who bases their cycles on just proviron or masteron?
plus, try telling anyone who suffers from deca-dick or tren-dick that they don't need test.... the response won't be pretty!
jnef
New member
njmuscleguy said:what other AAS are you suggesting that is "structurally and functionally similar enough to test" that you wouldn't need TEST? if you say DHT-derivitatves such as proviron and masteron, which are more androgenic than test (but not quite as anabolic), well who bases their cycles on just proviron or masteron?
plus, try telling anyone who suffers from deca-dick or tren-dick that they don't need test.... the response won't be pretty!
just throwing this out there...
eq/primo/mast
wouldnt that be a cycle that could do without test?

njmuscleguy said:ABSOLUTELY! In fact, HRT (hormone replacement therapy) dosage of test in most cases is 100-150mg per week. So if you're taking 150-200mg, then you're definitely ensuring that you're supplying what your body would be making naturally (that is, if you're healthy and have no hormonal deficiencies).
Over the years, dosages of *all* AAS have drastically increased... people think that you need alot more in order to get any kind of results. Simply not true. You can still get great results at lower, more modest dosages provided your training and diet are in check.
+1
My first cycle was 250 test and 20mg dbol ED. I made awesome gains, and it was very low dose.
njmuscleguy
New member
JNEF said:just throwing this out there...
eq/primo/mast
wouldnt that be a cycle that could do without test?
I don't have any experience with any of those... my understanding is that people can have libido issues with EQ, plus anxiety issues... according to Nelson, primo neither raises or lowers test levels, so I'm not sure if it's a suitable "replacement" to test... I can see masteron / proviron as a substitute for test in that they could help boost libido, but their gains in no way compare to test.
Tatyana
Elite Mentor
njmuscleguy said:what other AAS are you suggesting that is "structurally and functionally similar enough to test" that you wouldn't need TEST? if you say DHT-derivitatves such as proviron and masteron, which are more androgenic than test (but not quite as anabolic), well who bases their cycles on just proviron or masteron?
plus, try telling anyone who suffers from deca-dick or tren-dick that they don't need test.... the response won't be pretty!
I did read a bit of an endo text this afternoon.
If I remember this correctly, DHT and test have the same affinity for the androgen receptors in muscle tissues, it varies quite considerably in other tissues.
Tatyana
Elite Mentor
Ross said:AR-binding is only one pathway for anabolism, some steroids(such as Dianabol) barely bind to the A-R at all and yet are still extremely anabolic.
In terms of HPTA inhibition, each steroid has different binding affinity for the Androgen/Estrogen/Progesterone receptors. Steroids which ACTIVATE these receptors(bind) cause greater HPTA inhibition than those that do not.
Elaborate on the bits in bold please.
I am especially interested in the affinity of the different steroids for androgen (or other sex hormone receptors).
I did a wee bit of a search and couldn't find anything.

Mavafanculo
New member
once you start a cycle at high enough total levels, your body will cease producing its own test or cut back severely. some compounds are more suppressive than others, but at the doses an intermediate level BB would take you'll likely end up shut down.
I cant take it down to a molecule level, but going by my own experience and that of others that I've talked to or read about, you just never feel quite right without some Test cruising tru your system.
even supplying dht via masteron or proviron doesnt get it quite right mentally or physically. I've tried.
It might be the absence of metabolites that only reduce from test? might even be the small amount of estrogen that aromatized test will provide. dont know. there's alot the scientific community doesnt know about how and why drugs do all of what they do, and steroids are no exception.
absent any studies one way or the other, my opinion is just err on the side of safety and always add at least a replacement dose of test to a suppressive cycle (200-300 mg weekly). It doesnt need to be the base compound, just needs to be in there.
I cant take it down to a molecule level, but going by my own experience and that of others that I've talked to or read about, you just never feel quite right without some Test cruising tru your system.
even supplying dht via masteron or proviron doesnt get it quite right mentally or physically. I've tried.
It might be the absence of metabolites that only reduce from test? might even be the small amount of estrogen that aromatized test will provide. dont know. there's alot the scientific community doesnt know about how and why drugs do all of what they do, and steroids are no exception.
absent any studies one way or the other, my opinion is just err on the side of safety and always add at least a replacement dose of test to a suppressive cycle (200-300 mg weekly). It doesnt need to be the base compound, just needs to be in there.
Last edited:
jnef
New member
Mavafanculo said:Tat;
once you start a cycle at high enough total levels, your body will cease producing its own test or cut back severely. some compounds are more suppressive than others, but at the doses an intermediate level BB would take you'll likely end up shut down.
I cant take it down to a molecule level, but going by my own experience and that of others that I've talked to or read about, you just never feel quite right without some Test cruising tru your system.
even supplying dht via masteron or proviron doesnt get it quite right mentally or physically. I've tried.
It might be the absence of metabolites that only reduce from test? might even be the small amount of estrogen that aromatized test will provide. dont know. there's alot the scientific community doesnt know about how and why drugs do all of what they do, and steroids are no exception.
absent any studies one way or the other, my opinion is just err on the side of safety and always add at least a replacement dose of test to a suppressive cycle (200-300 mg weekly). It doesnt need to be the base compound, just needs to be in there.
lol here i thought i was setting myself up to get flamed with this post but damn turned out to be quite a post i learned a lot from - thanks everybody
Tatyana said:Elaborate on the bits in bold please.
I am especially interested in the affinity of the different steroids for androgen (or other sex hormone receptors).
I did a wee bit of a search and couldn't find anything.
This is textbook Endocrinology 101; The hypothalamus contains ANDROGEN, ESTROGEN, and PROGESTERONE receptors. Each anabolic steroid has different binding properties.
For example, Testosterone activates the Androgen and Estrogen receptors in the Hypothalamus and thus causes HPTA Shutdown. Trenbolone activates the Androgen and Progesterone receptors and thus causes HPTA shutdown. Primobolan and Anavar however, barely activate the Androgen receptors and have NO effect on estrogen or progesterone receptors and thus, DO NOT cause HPTA shutdown.
Mavafanculo
New member
Ross said:This is textbook Endocrinology 101; The hypothalamus contains ANDROGEN, ESTROGEN, and PROGESTERONE receptors. Each anabolic steroid has different binding properties.
For example, Testosterone activates the Androgen and Estrogen receptors in the Hypothalamus and thus causes HPTA Shutdown. Trenbolone activates the Androgen and Progesterone receptors and thus causes HPTA shutdown. Primobolan and Anavar however, barely activate the Androgen receptors and have NO effect on estrogen or progesterone receptors and thus, DO NOT cause HPTA shutdown.
^^ true - and most only focus on the estrogen negative feedback loop portion of the equation.
but as to var and primo barely binding to any of the receptors at he hypothalmus, that would also mean the same in muscle tissue receptors.
at levels high enough to sufficiently stimulate protein synthesis at the muscle, you'll also sufficiently stimulate the androgen receptor at the hypothalmus to cause suppression.
just going from my experience for example, var at 100+ mg daily made the boys disappear, and resulted in a crash if I tried to go without PCT
Tatyana
Elite Mentor
Ross said:This is textbook Endocrinology 101; The hypothalamus contains ANDROGEN, ESTROGEN, and PROGESTERONE receptors. Each anabolic steroid has different binding properties.
For example, Testosterone activates the Androgen and Estrogen receptors in the Hypothalamus and thus causes HPTA Shutdown. Trenbolone activates the Androgen and Progesterone receptors and thus causes HPTA shutdown. Primobolan and Anavar however, barely activate the Androgen receptors and have NO effect on estrogen or progesterone receptors and thus, DO NOT cause HPTA shutdown.
No offense hun, but 'this is endocrinology 101' that does come across as being a bit condescending.
Especially as you still haven't stated what your formal education is in.
Molecular biology, especially cell cycle control and cell signalling really rocks my world, and I have studied it extensively.
The text in bold is not in endocrinology textbooks.
I am looking for a table, some numbers, a paper.
This is the sort of stuff that is in basic endocrinology textbooks, synthesis pathways and signalling pathways (MAP-kinase and tyrosine kinase, C-AMP and G-AMP).


gjohnson5
New member
I like those charts. They show the metabolism of hormones and the enzymes which cause the catalytic reaction to convert Hormone A to Hormone B. It's also good that it shows cholesterol being converted to pregnenolone and the multiple pathways in which hormones can be created from pregnenolone. I wish it listed the names of the metabolic pathways themselves.
*edit*
I may want to find one of those which start at the testes and shows testosterone being secreted from the testes after interaction with LH and FSH from the pituitary to diagram out HPTA
*edit*
*edit*
I may want to find one of those which start at the testes and shows testosterone being secreted from the testes after interaction with LH and FSH from the pituitary to diagram out HPTA
*edit*
Tatyana
Elite Mentor
gjohnson5 said:I like those charts. They show the metabolism of hormones and the enzymes which cause the catalytic reaction to convert Hormone A to Hormone B. It's also good that it shows cholesterol being converted to pregnenolone and the multiple pathways in which hormones can be created from pregnenolone. I wish it listed the names of the metabolic pathways themselves.
*edit*
I may want to find one of those which start at the testes and shows testosterone being secreted from the testes after interaction with LH and FSH from the pituitary to diagram out HPTA
*edit*
I did see one of those in my recent searches, I will see if I can find it again.
I have more elaborate description/diagrams of sex hormone synthesis, but they are in textbooks.
Mavafanculo
New member
Tatyana said:Elaborate on the bits in bold please.
I am especially interested in the affinity of the different steroids for androgen (or other sex hormone receptors).
I did a wee bit of a search and couldn't find anything.
Thats a great question.
its one of those things that is included in every steroid profile on any site or book, and everyone takes for granted as an article of faith, but I havent seen (or noticed) the source for the assertions. (ie. "this steroid or that one has a strong binding affinity for this or that receptor")
soooo, who better to ask than one of our new COTB who has written many of the best steroid profiles avaiable to us. That would be Bill Llewellyn
Mavafanculo said:Thats a great question.
its one of those things that is included in every steroid profile on any site or book, and everyone takes for granted as an article of faith, but I havent seen (or noticed) the source for the assertions. (ie. "this steroid or that one has a strong binding affinity for this or that receptor")
soooo, who better to ask than one of our new COTB who has written many of the best steroid profiles avaiable to us. That would be Bill Llewellyn
There is not much data available, but I have composed a list based on the known properties of each anabolic steroid compound.
The Following drugs either DIRECTLY or INDIRECTLY activate ESTROGEN receptors, to varying degrees:
Testosterone
Methandrostenolone
Mathandriol
Oxymetholone
Nandrolone
Boldenone
The Following drugs either DIRECTLY or INDIRECTLY activate PROGESTERONE receptors, to varying degrees:
Nandrolone
Trenbolone
Oxymetholone
The Following drugs activate Androgen receptors, to varying degrees:
Testosterone
Methandrostenolone
Mathandriol
Oxymetholone
Nandrolone
Boldenone
Trenbolone
Halotestin
Oxandrolone
Stanzolol
Chlorodehydromethltestosterone
Methyltestosterone
Methenolone...
(ALL AAS*)
As we can see, the steroids that cause HPTA SHUTDOWN either OVERSATURATE ONE SPECIFIC receptor, or they activate too many TOTAL receptors(Androgen/Estrogen/Progesterone)
For instance, Trenbolone causes HPTA SHUTDOWN because it OVERSATURATES BOTH, the ANDROGEN and the PROGESTERONE receptors. Testosterone causes SHUTDOWN because it converts to ESTROGEN and DHT, therefore, it oversaturates the Androgen/Estrogen receptors.
As we can ALSO SEE, the steroids that DO NOT cause SHUTDOWN of the HPTA, do NOT oversaturate ANY of the different hormone receptors, and thus, do NOT cause SHUTDOWN. Methenolone(Primobolan) does not possess ANY Estrogenic or Progestational ACTIVITY WHATSOEVER. It does, by virtue of being an anabolic steroid, posses a SMALL Androgenic component. Because it lacks ANY ESTROGENIC/PROGESTATIONAL component, and it lacks a strong Androgenic component, it WILL NOT CAUSE SHUTDOWN! Oxandrolone(Anavar) posseses NO Estrogenic/Progestational component either. AND, it also lacks a strong androgenic component. Thus, Anavar will NOT cause shutdown.
Mavafanculo
New member
Ross said:........As we can ALSO SEE, the steroids that DO NOT cause SHUTDOWN of the HPTA, do NOT oversaturate ANY of the different hormone receptors, and thus, do NOT cause SHUTDOWN. Methenolone(Primobolan) does not possess ANY Estrogenic or Progestational ACTIVITY WHATSOEVER. It does, by virtue of being an anabolic steroid, posses a SMALL Androgenic component. Because it lacks ANY ESTROGENIC/PROGESTATIONAL component, and it lacks a strong Androgenic component, it WILL NOT CAUSE SHUTDOWN!
Oxandrolone(Anavar) posseses NO Estrogenic/Progestational component either. AND, it also lacks a strong androgenic component. Thus, Anavar will NOT cause shutdown.
you calling my nads liars? lol
----------
Clin Endocrinol (Oxf). 1997 Feb;46(2):209-16.
Effect of low dose oxandrolone and testosterone treatment on the pituitary-testicular and GH axes in boys with constitutional delay of growth and puberty.
Crowne EC, Wallace WH, Moore C, Mitchell R, Robertson WH, Holly JM, Shalet SM.
Department of Endocrinology, Christie Hospital Trust, Manchester, UK.
OBJECTIVE: To investigate the effect of low dose oxandrolone and testosterone on the pituitary-testicular and GH-IGF-I axes. DESIGN: Prospective double-blind placebo-controlled trial. PATIENTS: Sixteen boys with constitutional delay of growth and puberty (CDGP) with testicular volumes 4-6 ml were randomized to 3 months treatment: Group 1 (n = 5), daily placebo: Group 2 (n = 5), 2.5 mg oxandrolone daily or Group 3 (n = 6), 50 mg testosterone monthly intramuscular injections with assessment (growth, pubertal development and overnight hormone profiles) at 0, 3, 6 and 12 months. MAIN OUTCOME MEASURES: LH and GH profiles (15-minute samples) were analysed by peak detection (Pulsar), Fourier transformation and autocorrelation. Testosterone levels were measured hourly and insulin, SHBG, IGF-I, and IGFBP-3 levels at 0800 h. Statistical analysis was by multivariate analysis of variance for repeated measures. RESULTS: LH and testosterone parameters increased significantly with time in all 16 (LH AUC, P < 0.001; peak amplitude, P = 0.02; number of peaks, P = 0.02; testosterone AUC, P = 0.02; morning testosterone, P = 0.002). In Group 2, however, LH and testosterone parameters decreased at 3 months followed by a rebound increase at 6 and 12 months. SHBG levels were markedly reduced at 3 months (P = 0.006) and a wider range of dominant GH frequencies was present although GH AUC was not increased until 6 months, with an increase in GH pulse frequency but not amplitude. IGF-I levels were increased at both 3 and 12 months. In Group 3, pituitary-testicular suppression was not apparent, but GH levels increased with an increase in GH amplitude at 3 and 12 months. CONCLUSION: Oxandrolone transiently suppressed the pituitary-testicular axis and altered GH pulsatility. Testosterone increased GH via amplitude modulation.
-----------
also, this suppression was at baby sized doses. BB's take up to FIFTY times the study dose.
gjohnson5
New member
I agree that the steroid profiles have marginal accuracy since there are very few human studies on this stuff. The other portion of the data is based on mice and rat studies since noone gives a fuck about the long terms effects of studies on lab rodents.... We should most definitly be studying the long term effects of steroid medication/use/abuse on humans IMHO. But some people are still basing what they say on some of the Dan Duchaine work because he would inject heavy dosages of steroid and in a marginally accurate way publish data about the changes he noticed in his genetics. But there is no profit potential in investigating this stuff until we vote in politicians who are pro-steroid use and get the Scheduled drug stuff overturned.
Mavafanculo said:Thats a great question.
its one of those things that is included in every steroid profile on any site or book, and everyone takes for granted as an article of faith, but I havent seen (or noticed) the source for the assertions. (ie. "this steroid or that one has a strong binding affinity for this or that receptor")
soooo, who better to ask than one of our new COTB who has written many of the best steroid profiles avaiable to us. That would be Bill Llewellyn
Mavafanculo said:you calling my nads liars? lol
Clin Endocrinol (Oxf). 1997 Feb;46(2):209-16.
Effect of low dose oxandrolone and testosterone treatment on the pituitary-testicular and GH axes in boys with constitutional delay of growth and puberty.
Crowne EC, Wallace WH, Moore C, Mitchell R, Robertson WH, Holly JM, Shalet SM.
Department of Endocrinology, Christie Hospital Trust, Manchester, UK.
OBJECTIVE: To investigate the effect of low dose oxandrolone and testosterone on the pituitary-testicular and GH-IGF-I axes. DESIGN: Prospective double-blind placebo-controlled trial. PATIENTS: Sixteen boys with constitutional delay of growth and puberty (CDGP) with testicular volumes 4-6 ml were randomized to 3 months treatment: Group 1 (n = 5), daily placebo: Group 2 (n = 5), 2.5 mg oxandrolone daily or Group 3 (n = 6), 50 mg testosterone monthly intramuscular injections with assessment (growth, pubertal development and overnight hormone profiles) at 0, 3, 6 and 12 months. MAIN OUTCOME MEASURES: LH and GH profiles (15-minute samples) were analysed by peak detection (Pulsar), Fourier transformation and autocorrelation. Testosterone levels were measured hourly and insulin, SHBG, IGF-I, and IGFBP-3 levels at 0800 h. Statistical analysis was by multivariate analysis of variance for repeated measures. RESULTS: LH and testosterone parameters increased significantly with time in all 16 (LH AUC, P < 0.001; peak amplitude, P = 0.02; number of peaks, P = 0.02; testosterone AUC, P = 0.02; morning testosterone, P = 0.002). In Group 2, however, LH and testosterone parameters decreased at 3 months followed by a rebound increase at 6 and 12 months. SHBG levels were markedly reduced at 3 months (P = 0.006) and a wider range of dominant GH frequencies was present although GH AUC was not increased until 6 months, with an increase in GH pulse frequency but not amplitude. IGF-I levels were increased at both 3 and 12 months. In Group 3, pituitary-testicular suppression was not apparent, but GH levels increased with an increase in GH amplitude at 3 and 12 months. CONCLUSION: Oxandrolone transiently suppressed the pituitary-testicular axis and altered GH pulsatility. Testosterone increased GH via amplitude modulation.
-
EXACLTY!! Oxandrolone does not SHUTDOWN the HPTA, it DOES reduce endogenous testosterone production, obviously.
TRENBOLONE and DECA will SHUTDOWN the HPTA, Oxandrolone and Primo will NOT.*
Harleymarleybone
New member
njmuscleguy said:what other AAS are you suggesting that is "structurally and functionally similar enough to test" that you wouldn't need TEST? if you say DHT-derivitatves such as proviron and masteron, which are more androgenic than test (but not quite as anabolic), well who bases their cycles on just proviron or masteron?
plus, try telling anyone who suffers from deca-dick or tren-dick that they don't need test.... the response won't be pretty!
I thought the issue is what you can do, not what people actually base their cycles on, since what they actually base their cycles on might itself be the premise that is being questioned- that you always need test.
The fact that you may need test with nandrolones does not contradict what I said about some AAS. Also, I have done deca with only 100 mg/week (TRT dose) and was fine.
Mavafanculo
New member
Ross said:EXACLTY!! Oxandrolone does not SHUTDOWN the HPTA, it DOES reduce endogenous testosterone production, obviously.
TRENBOLONE and DECA will SHUTDOWN the HPTA, Oxandrolone and Primo will NOT.*
other than that mrs lincoln how was the play?
if you're arguing a distinction between lowered LH , lowered endogenous test, pituitery suppression and hpta suppression you'll have to elaborate. If there is a distinction, its a distinction without a difference.
from the study (group 2 is the OX group):
In Group 2, however, LH and testosterone parameters decreased at 3 months
this is the clinical end result of hpta suppression.
Mavafanculo said:other than that mrs lincoln how was the play?
if you're arguing a distinction between lowered LH , lowered endogenous test, pituitery suppression and hpta suppression you'll have to elaborate. If there is a distinction, its a distinction without a difference.
from the study (group 2 is the OX group):
In Group 2, however, LH and testosterone parameters decreased at 3 months
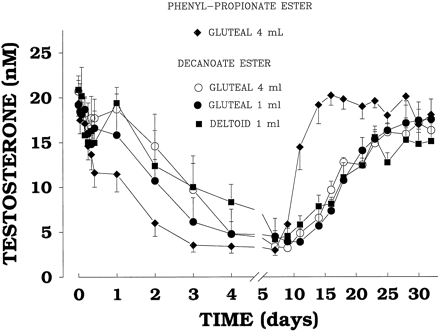
We can see from the chart above that a simgle 100mg injection of Deca caused a total (100%) reduction of natural testosterone levels, and it took about a month to return those testosterone levels to baseline! All from 100mgs of Deca!
Mavafanculo
New member
Ross said:
We can see from the chart above that a simgle 100mg injection of Deca caused a total (100%) reduction of natural testosterone levels, and it took about a month to return those testosterone levels to baseline! All from 100mgs of Deca!
this goes to deca being very suppressive - I agree.
but you asserted that var was NOT suppressive, and the study above shows that it is. that was my point - not relative suppressivity. I agree that deca does the deed faster and at lower doses.
gjohnson5
New member
Wow , taking charts from AR are we?
What study or journal did that chart come from?
Also we'd need anavar diagrammed as well in it
But we'd need a longer term one of these to see if testosterone is totally shutdown. At this point this is a semantic arguement as to the meaning of "HPTA supression" If this dose was tripled would the supression triple? Unfortunately the boys liver would be hurt severly in the process...

http://jcem.endojournals.org/cgi/co...INDEX=0&sortspec=relevance&resourcetype=HWCIT
Serum OX concentrations on day 3 (1.9 ± 0.4 ng/dL) and day 5 (2.2 ± 0.3 ng/dL) of OX administration, measured 10 h after each evening’s oral dose (2100 h), remained steady. However, by 18 h posttreatment on day 5, serum OX levels were markedly reduced (0.48 ± 0.06 ng/dL; P < 0.01) compared to day 3 or day 5 10-h values. Total serum T concentrations were within normal physiological range on day 0 (449 ± 35 ng/dL) and day 3 (441 ± 44 ng/dL) of OX treatment. However, by day 5, total serum T concentrations were significantly reduced (282 ± 45 ng/dL; P < 0.05) below day 0 and day 3 values (Fig. 3Go). Serum free T concentrations were within normal physiological range on days 0, 3, and 5. However, by day 5, serum free T concentrations were significantly reduced (98 ± 10 pg/mL; P < 0.001) below day 0 (121 ± 12 pg/mL) and day 3 (126 ± 9 pg/mL) values. Hence, the total androgen concentration (T + OX) was reduced in parallel to the reduction in T (Fig. 3Go).
What study or journal did that chart come from?
Also we'd need anavar diagrammed as well in it
But we'd need a longer term one of these to see if testosterone is totally shutdown. At this point this is a semantic arguement as to the meaning of "HPTA supression" If this dose was tripled would the supression triple? Unfortunately the boys liver would be hurt severly in the process...
http://jcem.endojournals.org/cgi/co...INDEX=0&sortspec=relevance&resourcetype=HWCIT
Serum OX concentrations on day 3 (1.9 ± 0.4 ng/dL) and day 5 (2.2 ± 0.3 ng/dL) of OX administration, measured 10 h after each evening’s oral dose (2100 h), remained steady. However, by 18 h posttreatment on day 5, serum OX levels were markedly reduced (0.48 ± 0.06 ng/dL; P < 0.01) compared to day 3 or day 5 10-h values. Total serum T concentrations were within normal physiological range on day 0 (449 ± 35 ng/dL) and day 3 (441 ± 44 ng/dL) of OX treatment. However, by day 5, total serum T concentrations were significantly reduced (282 ± 45 ng/dL; P < 0.05) below day 0 and day 3 values (Fig. 3Go). Serum free T concentrations were within normal physiological range on days 0, 3, and 5. However, by day 5, serum free T concentrations were significantly reduced (98 ± 10 pg/mL; P < 0.001) below day 0 (121 ± 12 pg/mL) and day 3 (126 ± 9 pg/mL) values. Hence, the total androgen concentration (T + OX) was reduced in parallel to the reduction in T (Fig. 3Go).
njmuscleguy
New member
Ross said:Proviron and Masteron can be used INSTEAD OF TESTOSTERONE, as I have already stated.
The ANDROGENIC component possessed by these two compounds will increase MOOD, LIBIDO, and ENERGY.
So you're saying that proviron or masteron are not as suppressive as test yet will give the same FEEL that test does?
From what I've read, proviron has a decent androgen rating... even if it is considered "weak" (that's because it's not as anabolic). And from personal experience, I can FEEL that proviron is fairly androgenic....especially when the typical androgen sides start up (prostate issues, acne, hair loss). True, proviron is not as androgenic as say tren, but I'm not sure that using proviron or materon is a good argument for those looking for minimal suppression / shutdown in comparison to using test. Just my uneducated opinion.
Tatyana said:I did see one of those in my recent searches, I will see if I can find it again.
I have more elaborate description/diagrams of sex hormone synthesis, but they are in textbooks.


Sports Med 2004; 34 (8): 513-554
Effects of Androgenic-Anabolic Steroids in Athletes
Mavafanculo said:this goes to deca being very suppressive - I agree.
but you asserted that var was NOT suppressive, and the study above shows that it is. that was my point - not relative suppressivity. I agree that deca does the deed faster and at lower doses.
ALL steroids are suppressive(in high enough dosages), I never said Anavar was not suppressive, I said it would not oversaturate the Androgen and Estrogen receptors in the hypothalamus and would thus not cause complete HPTA shutdown, which IS a very important physiological distinction.
Mavafanculo
New member
Ross said:ALL steroids are suppressive(in high enough dosages), I never said Anavar was not suppressive, I said it would not oversaturate the Androgen and Estrogen receptors in the hypothalamus and would thus not cause complete HPTA shutdown, which IS a very important physiological distinction.
I'd have to dig further for confirming studys, but it seems only logical that if a baby-sized dose of 2.5 mg of var will suppress, given how homeostatsis works with the body trying to reduce endogenous test proportionate to exogenous test-mapped substance introduced, that then an 80 or 100 or 150mg dose of var (which is what BB's typically use) will further suppress to the point of "shutdown".
its just a continuum. "shutdown" is just another way of saying 99%-100% "suppressed".
In the meantime, everybody give the guy who started this thread some K lol.
There are very few studies on how these sopposed "suppreissive compounds" are infact suppressive and dont cause total shutdown themselves. There are one or two studies (one on dianabol 100mg/ED for an extended peroid) that states HPTA shutdown wasnt achieved. But the other compounds in Ross's list there is no clinical data.
Bodybuilders use different doses to ones used for aid and cancer patients, therfore its more of a guesing game on whats "suppresive" and whats not.
There are a number of studies that state Anavar (very low dose) was fairly suppressive to the HPTA (40% I believe) so what sort of inhibtion can one expect on 60mg/ED for 6-8 weeks. There is also a study on Winstrol stating the same.
When combining "suppressive compounds" this conclusion of "suppression, not shutdown" become even more hazardous.
Androgens can also be directly inhibtiive to the pituitary and leydig cells, which Ross's theory doesnt comprehend. Though this is a subject no-one fully understands yet.
I've spoken with an Endo regarding these theories and other theory's Ross has, which have been refuted.
Bodybuilders use different doses to ones used for aid and cancer patients, therfore its more of a guesing game on whats "suppresive" and whats not.
There are a number of studies that state Anavar (very low dose) was fairly suppressive to the HPTA (40% I believe) so what sort of inhibtion can one expect on 60mg/ED for 6-8 weeks. There is also a study on Winstrol stating the same.
When combining "suppressive compounds" this conclusion of "suppression, not shutdown" become even more hazardous.
Androgens can also be directly inhibtiive to the pituitary and leydig cells, which Ross's theory doesnt comprehend. Though this is a subject no-one fully understands yet.
I've spoken with an Endo regarding these theories and other theory's Ross has, which have been refuted.
Tatyana
Elite Mentor
Ross said:There is not much data available, but I have composed a list based on the known properties of each anabolic steroid compound.
The Following drugs either DIRECTLY or INDIRECTLY activate ESTROGEN receptors, to varying degrees:
Testosterone
Methandrostenolone
Mathandriol
Oxymetholone
Nandrolone
Boldenone
The Following drugs either DIRECTLY or INDIRECTLY activate PROGESTERONE receptors, to varying degrees:
Nandrolone
Trenbolone
Oxymetholone
The Following drugs activate Androgen receptors, to varying degrees:
Testosterone
Methandrostenolone
Mathandriol
Oxymetholone
Nandrolone
Boldenone
Trenbolone
Halotestin
Oxandrolone
Stanzolol
Chlorodehydromethltestosterone
Methyltestosterone
Methenolone...
(ALL AAS*)
As we can see, the steroids that cause HPTA SHUTDOWN either OVERSATURATE ONE SPECIFIC receptor, or they activate too many TOTAL receptors(Androgen/Estrogen/Progesterone)
For instance, Trenbolone causes HPTA SHUTDOWN because it OVERSATURATES BOTH, the ANDROGEN and the PROGESTERONE receptors. Testosterone causes SHUTDOWN because it converts to ESTROGEN and DHT, therefore, it oversaturates the Androgen/Estrogen receptors.
As we can ALSO SEE, the steroids that DO NOT cause SHUTDOWN of the HPTA, do NOT oversaturate ANY of the different hormone receptors, and thus, do NOT cause SHUTDOWN. Methenolone(Primobolan) does not possess ANY Estrogenic or Progestational ACTIVITY WHATSOEVER. It does, by virtue of being an anabolic steroid, posses a SMALL Androgenic component. Because it lacks ANY ESTROGENIC/PROGESTATIONAL component, and it lacks a strong Androgenic component, it WILL NOT CAUSE SHUTDOWN! Oxandrolone(Anavar) posseses NO Estrogenic/Progestational component either. AND, it also lacks a strong androgenic component. Thus, Anavar will NOT cause shutdown.
I bounced this post off of a neuroscientist I know (that means he has a PhD), and he is a jooser and a mod on a fairly reknown BBing board.
This was his response:
--------------------------------------------------------------------------------
he's wrong on many levels. However, some drugs will not shut you down completely. thats the only point he makes in the beginning, but he doesn't really understand what is known and not known about feed back to the hypothalamus.
Tatyana said:I bounced this post off of a neuroscientist I know (that means he has a PhD), and he is a jooser and a mod on a fairly reknown BBing board.
This was his response:
--------------------------------------------------------------------------------
he's wrong on many levels. However, some drugs will not shut you down completely. thats the only point he makes in the beginning, but he doesn't really understand what is known and not known about feed back to the hypothalamus.
He does know that we are talking about receptors in the Hypothalamus, correct?
Tatyana
Elite Mentor
Ross said:He does know that we are talking about receptors in the Hypothalamus, correct?
Yes Ross, he has a PhD in neuroscience and is a research scientist.
The whole hypothalamus-anterior/posterior pituitary thing and all the trophic releasing factors and negative feedback regulation.
Do you know which hormone in the pituitary has a positive feedback mechanism as you have been educating people in endocrinology 101?
What did you study at Uni BTW?
Ross said:
We can see from the chart above that a simgle 100mg injection of Deca caused a total (100%) reduction of natural testosterone levels, and it took about a month to return those testosterone levels to baseline! All from 100mgs of Deca!
What? A complete 100% shutdown would mean that those little dot thigns on the graph go to zero. They do not. Everyone's just arguing degrees of suppression here, not "total reduction".
Twenty nm to 5 nm is a 75% reduction.
Therefore, we can conclude that deca "does not SHUTDOWN the HPTA, it DOES reduce endogenous testosterone production, obviously".
And ditto that the pretty excell chart had no reference or source. I can easily make a chart saying anything I want, host it online, then use it to push my arguments.


Tatyana said:Yes Ross, he has a PhD in neuroscience and is a research scientist.
The whole hypothalamus-anterior/posterior pituitary thing and all the trophic releasing factors and negative feedback regulation.
Do you know which hormone in the pituitary has a positive feedback mechanism as you have been educating people in endocrinology 101?
What did you study at Uni BTW?
ummm, i believe this is what they call: "game, set, match...next player"

Last edited:
eddymerckx said:ummm, i believe this is what they call: "game, sat, match...next player"

digitizedsoul
New member
 tat
eddymerckx said:ummm, i believe this is what they call: "game, set, match...next player"
Dont really want to bump this, but I just read this whole thing. Just thought it was interesting he didn't respond after that.
Similar threads

- Replies
- 16
- Views
- 787


- Replies
- 8
- Views
- 260
- Replies
- 13
- Views
- 662
- Replies
- 4
- Views
- 230
